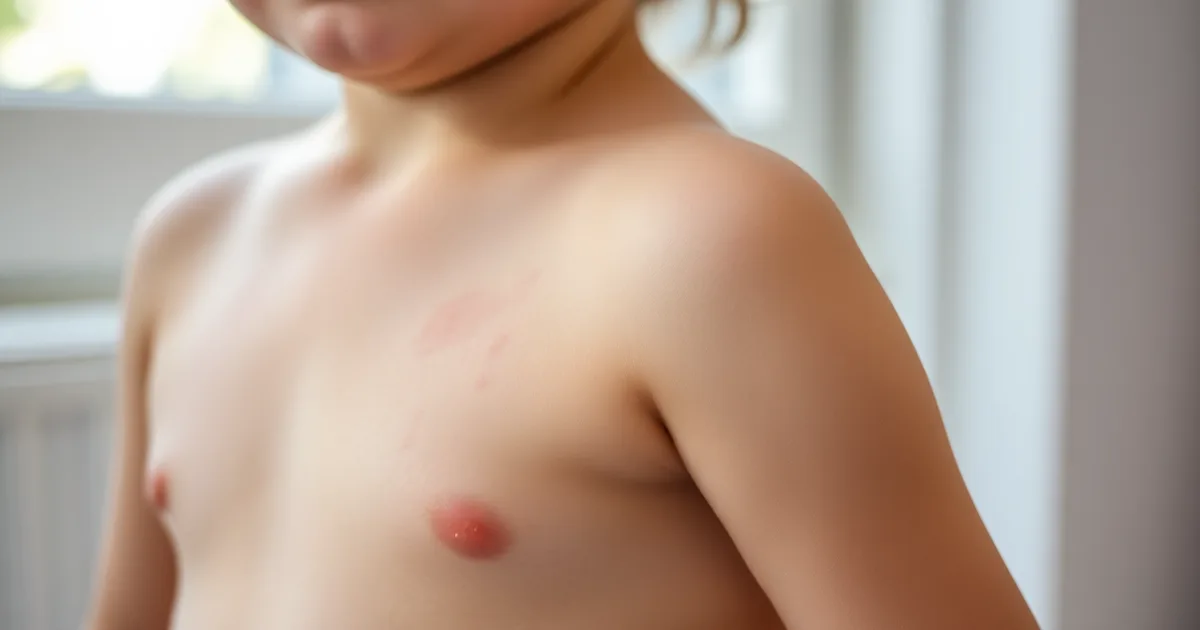
An amoxicillin rash is usually not a true allergy. It typically shows up 5 to 10 days after the first dose, looks flat or slightly raised, blanches when pressed, and spares the mouth, eyes and genitals. A real penicillin allergy often starts within 1 to 72 hours, may be hives, and can bring swelling or breathing trouble.
So the reflex to bin the bottle is understandable, and often wrong. Up to 10% of children taking amoxicillin develop a rash that has nothing to do with IgE, and fewer than 1 in 10 of those children turn out to be genuinely penicillin-allergic on testing. The rest get labelled for life over what was a predictable drug eruption. That label follows them into every future prescription, which is how people end up on broader-spectrum antibiotics they did not need.
Which is why the instruction on the box still holds: never stop a prescribed antibiotic without contacting a clinician. An untreated ear infection, pneumonia or strep throat carries its own risks, and some of them are worse than a spotted trunk. Call the prescriber, describe the timing and appearance, and let them decide whether to continue, switch or assess.
There are exceptions, and they are not subtle. Mucosal sores, blistering, skin that hurts to touch, fever above 38°C (100.4°F), facial swelling or any trouble breathing mean stop the drug and get emergency care, because those point toward the severe cutaneous adverse reactions the NIH/NIAID drug allergy guidelines group under SCARs.
- Timing separates them: benign delayed amoxicillin rash appears 5 to 10 days after the first dose, occasionally up to 14, while immediate IgE-mediated penicillin reactions usually begin within 1 to 6 hours and no later than 72 hours.
- Most rashes aren't allergy: roughly 10% of children on amoxicillin break out, yet fewer than 1 in 10 of those rashes represent true penicillin allergy.
- Blanching and sparing: a benign eruption fades under pressure and leaves the mouth, eyes and genitals alone, whereas hives, mucosal involvement or skin pain point the other way.
- Emergency features: mucosal sores, blistering, skin pain, fever over 38°C (100.4°F), facial swelling or breathing difficulty mean stop the drug and seek urgent care the same day.
- Testing exists: penicillin skin testing plus a direct oral amoxicillin challenge, done after the rash clears, is the standard way to confirm or rule out the allergy for good.
What does an amoxicillin rash usually look like, and when does it show up?
The benign, non-allergic reaction has a signature: it shows up 5–10 days after the first dose. Some case series stretch that window to 14 days. That delay is the whole point. It is a T-cell–driven eruption, not the IgE-mediated reaction people picture when they hear "penicillin allergy" — immediate reactions land within 1–6 hours of a dose, and virtually always inside 72 hours.
What you see is a maculopapular rash: flat or slightly raised pink-to-red spots, roughly 1–5 mm across, that merge into blotchy patches. Press a glass tumbler against one and it fades — that blanching is the single most useful bedside sign, because it means blood is still flowing normally under the skin rather than leaking into it. It usually starts on the trunk or in the armpits and groin creases, then spreads outward across the limbs over a day or two. Mucous membranes are spared. Mouth, eyes and genitals stay clear, which is exactly why involvement of any of those areas is a red flag rather than a variation on the theme.
Itching and the timing trap
Itching is common and varies enormously — some people barely notice it, others scratch through the night. Pain is not part of the picture. If the skin hurts to touch, or feels tight and burning, that points somewhere else entirely.
Timing is the trap. Parents often blame the first dose, but by day seven the child has usually been on amoxicillin for a week, and the rash appears while they also have a viral illness — which is the actual trigger in a large share of cases. Roughly 10% of children develop a rash while taking amoxicillin, and fewer than 1 in 10 of those rashes turn out to be true penicillin allergy on proper assessment. Epstein-Barr virus is the classic co-conspirator: amoxicillin given during acute EBV infection produces a rash in a high proportion of patients who are not and never will be penicillin-allergic. That distinction matters later, because a mislabelled allergy follows people into every future hospital admission.
How is a true penicillin allergy rash different from an amoxicillin rash?
The clock is the most useful tool you have. A benign amoxicillin rash almost always appears between 5 and 10 days after the first dose, though case series have reported onsets as late as 14 days. True IgE-mediated penicillin allergy looks nothing like that: it shows up within 1 to 6 hours of a dose, and never later than 72 hours. If your rash started three days into treatment and you have no other symptoms, you are looking at the benign pattern.
Morphology matters almost as much as timing. A benign delayed rash is maculopapular — flat red patches and small raised bumps, usually starting on the trunk and spreading outward, sometimes itching. Hives are different: raised, pale-centred welts that move around the body within hours, often with swelling of the lips, eyelids or tongue. That is urticaria, and it points to IgE.
| Feature | Benign amoxicillin rash | True penicillin allergy (IgE) | Severe delayed reaction (DRESS, SJS/TEN, AGEP) |
|---|---|---|---|
| Onset after first dose | 5–10 days (up to 14 days in some series) | 1–6 hours (hard ceiling of 72 hours) | 2–8 weeks |
| Lesion type | Maculopapular, flat-to-raised, trunk-first | Urticarial welts or angioedema | Blistering, sheet-like skin loss, or pustules on red skin |
| Fever | Absent | Absent | Present, often above 38°C (100.4°F) |
| Mucosal involvement | None | Lip or tongue swelling only, no ulceration | Sores in mouth, eyes or genitals |
| Skin pain or tenderness | Itch only | Itch, sometimes burning at hive sites | Painful skin, sometimes before any visible rash |
| Breathing or blood pressure | Normal | Wheeze, throat tightness, or faintness within minutes | Normal early, then systemic decline |
For the reader whose rash started on day 6, is flat-to-bumpy, itches, and comes with no fever, no mouth sores and no breathing change, the first column wins: this is the benign pattern, and roughly 9 in 10 rashes like this are not true penicillin allergy. That flips entirely if any single cell in the third column applies — skin pain with fever, mucosal blisters, or facial swelling with breathing difficulty means stop the drug now and go to emergency care, not to a search engine. One caveat on the first column: the 1–6 hour window only holds for the first dose of a course. If someone has been sensitised by earlier penicillin exposure, a reaction can appear within minutes of a repeat course years later, so timing is judged from the most recent dose, not the original prescription.
When amoxicillin rash is more likely because of an infection, not the drug
Epstein-Barr virus is the clearest example. Give amoxicillin to someone in the acute phase of infectious mononucleosis and a rash appears in roughly 30–90% of cases, depending on the case series — a rate far higher than the 10% background figure for children on amoxicillin generally. The mechanism is not IgE. EBV infects B cells and shifts the T cell response, and the drug appears to amplify that immune activation rather than trigger it. The same pattern shows up in cytomegalovirus, in acute HIV seroconversion, and in some cases of Mycoplasma pneumoniae.
Group A streptococcal pharyngitis can muddy things the same way. Scarlet fever produces a fine, sandpapery maculopapular rash that starts on the trunk and flexures and can look close enough to a drug eruption that a clinician working from a phone photo cannot separate them. If the rash appeared within 24–48 hours of the sore throat and fever rather than 5–10 days after the first amoxicillin dose, infection is the more likely driver, and the antibiotic is probably not the culprit.
Timing is the single most useful discriminator you have at home. A benign delayed amoxicillin rash typically shows up 5–10 days after the first dose, sometimes as late as 14 days in reported cases. An infection-related rash usually tracks the infection: it appears with or shortly after the fever and sore throat, not a week into treatment. If your child had a fever and swollen glands for three days, then started amoxicillin, then broke out on day two of the antibiotic, the infection was already running before the drug arrived.
Confirming an infection-related cause changes the downstream plan. If EBV or strep is documented, there is no indication for penicillin skin testing or a direct oral challenge — the rash was a predictable reaction to a drug-virus interaction, not an allergy, and it does not need an allergy workup. That matters because the CDC estimates about 90% of patients carrying a penicillin allergy label are not actually allergic on testing, and a label acquired this way is one of the main ways it happens. Document the context, not just "rash to amoxicillin," or the next clinician will treat it as a true allergy and reach for a broader-spectrum alternative.
Red flags that mean stop the antibiotic and get urgent help
The point of a red-flag list is not to diagnose anything. It is to split a phone-at-10pm decision into two piles: rashes that can wait for a clinic appointment, and rashes where the next dose should not be given because something other than a benign drug eruption is unfolding. Benign delayed amoxicillin rashes almost never do the things below.
- Sores or raw patches in the mouth, eyes, or genitals. Look inside the lips, under the tongue, and at the conjunctiva. Two or more mucosal surfaces involved points away from a simple maculopapular rash and toward Stevens-Johnson syndrome (SJS) or toxic epidermal necrolysis (TEN), both of which are medical emergencies. Do not give the next dose. Go to an emergency department, not an urgent care clinic.
- Blistering, skin peeling, or a positive Nikolsky sign. If gentle rubbing of apparently normal skin lifts the top layer, or if the rash is developing flaccid blisters or sheet-like detachment, that is TEN until proven otherwise. Mortality for TEN is commonly cited at 25–30%, and the timeline matters more than the size of the lesions on day one.
- Fever above 38°C (100.4°F) together with the rash. A low-grade fever can accompany a benign delayed exanthem, particularly in children with a concurrent viral illness. A fever that appears after the rash has already started, or that climbs above 38°C alongside facial swelling and rising inflammatory markers, is the pattern that triggers evaluation for DRESS. Same-day assessment, not next week.
- Facial swelling, lip or tongue swelling, wheezing, or trouble breathing. These are the immediate-type, IgE-mediated features, and they usually arrive within 1–6 hours of a dose, with 72 hours as the outer limit in current allergy guidelines. Use adrenaline auto-injector if one is prescribed, then call emergency services. This is the one presentation where minutes genuinely change the outcome.
- Dark urine, passing much less urine than usual, or yellowing of the eyes or skin. These are the hepatic and renal signals of DRESS (drug reaction with eosinophilia and systemic symptoms), which typically declares itself 2–8 weeks after starting the drug but can appear earlier. Bloodwork showing transaminitis or a rising creatinine is what confirms it. Dark tea-coloured urine in a child on amoxicillin is a same-day emergency visit.
- Skin that hurts to touch, or a rash that feels painful rather than itchy. Pain out of proportion to what the skin looks like is a recognised early warning in SJS and in staphylococcal scalded skin syndrome. Parents often report a child who will not tolerate a nappy change or a t-shirt touching the trunk. Trust that report.
- Rapid spread over hours, or a rash that turns purpuric. Non-blanching spots that do not fade under a glass tumbler, especially with fever and a child who looks unwell, need emergency assessment for meningococcal disease and other invasive infections. Amoxicillin at standard doses does not reliably cover meningococcus, so the drug is not a reason to wait.
The item people most often get wrong is fever. A temperature of 38.2°C in a child who is otherwise playful, eating, and four days into a maculopapular rash is not, on its own, a reason to abandon the antibiotic at midnight — that is the territory of the benign delayed eruption, which shows up in roughly 5–10 days in about 10% of children taking amoxicillin. What changes the calculation is fever plus any of the other six items, or fever in an adult, or fever that appears after the rash rather than alongside it. In those cases the answer is stop the dose and get seen. Roughly 90% of people carrying a penicillin allergy label are not actually allergic on testing, per CDC estimates, which is exactly why the decision should be made by someone who can examine the skin and order a blood count rather than by whoever is holding the phone.
Should you stop amoxicillin if a rash appears?
Use this sequence the moment a rash shows up during an amoxicillin course — most often on day 5 to day 10 after the first dose, though case series have reported benign delayed rashes starting as late as 14 days. You need three things before you decide anything: the time of the last dose, a phone, and a well-lit look at the skin including the mouth, eyes and genitals. The whole assessment below takes under five minutes, and the phone call that follows is free in most countries via a nurse advice line or the prescriber's out-of-hours number.
- Check for red flags first, before you touch the next dose. Stop the antibiotic and seek emergency care now if you see any of: blistering or peeling skin, sores or ulcers in the mouth, eyes or genitals, skin that hurts to touch, facial or tongue swelling, difficulty breathing or swallowing, fever above 38°C (100.4°F) with the rash, or a rash that spreads rapidly with a feeling of being very unwell. These point towards DRESS, Stevens-Johnson syndrome, toxic epidermal necrolysis or anaphylaxis — rare, but they move fast and the window for reversing them is short. Call emergency services rather than driving yourself if breathing is affected.
- If there are no red flags, call the prescriber or an advice line before the next scheduled dose — not after it. Ringing before the dose is the step most people skip, because the rash looks mild and the next dose is sitting there. Have the packet in your hand so you can read out the strength in mg and the exact dosing interval. Expect a callback within an hour on most national advice lines; if you cannot reach anyone and the next dose is due, hold the dose and keep trying rather than guessing. Holding one dose of amoxicillin for a few hours is low-risk. Giving a dose into an evolving systemic reaction is not.
- While you wait, write down what you are seeing. The clinician will ask four things: when the first dose was given, when the rash appeared, what it looks like now, and whether anything else changed. Note the timing against the two useful windows: 1 to 6 hours after a dose suggests an immediate IgE-mediated reaction, while 5 to 10 days after the first dose fits the far more common delayed T-cell-driven exanthem. Take two photos in daylight, one close and one showing the spread. Costs nothing, saves a repeat appointment.
- Note any other symptoms on the same page, separately from the rash. Itch without pain, no fever, and a child who is eating and playing normally reads very differently from a child with a temperature of 38.6°C, swollen glands and a sore mouth. Ask about joint aches, facial puffiness in the morning, and any reduction in urine output — these push the assessment towards a systemic drug reaction rather than a simple exanthem.
- Follow the advice you are given, which will usually be one of three paths. In the most common outcome, the clinician tells you to continue amoxicillin and add an oral antihistamine such as cetirizine or chlorphenamine for itch, with review in 24 to 48 hours. If the infection is not serious and the rash is troublesome, they may switch you to a non-penicillin antibiotic. If there is genuine concern, they stop the drug and arrange allergy assessment.
- If you are told to continue, set a check-in alarm for 24 hours. The rash should stop spreading and start fading; itch should settle within 30 to 60 minutes of an antihistamine dose. Escalate immediately if the rash becomes painful, blisters, or the fever climbs.
- If you are told to stop, ask what replaces the antibiotic. A stopped course for a chest or ear infection that is not covering another drug is a real risk, and roughly 90% of people labelled penicillin-allergic turn out not to be allergic on formal testing, according to CDC estimates. Ask for the label "amoxicillin rash, unspecified" rather than "penicillin allergy" in the notes — the wording affects every future prescription.
- Before you finish the call, ask whether allergy testing is worth arranging. Skin testing followed by a direct oral challenge in a supervised clinic takes two to three hours in one visit and resolves the question properly. Waiting lists vary; in many systems it is three to twelve months.
The failure mode here is reflexive stopping. Up to 10% of children develop a rash while taking amoxicillin, and fewer than 1 in 10 of those rashes represent true penicillin allergy — often the rash is driven by the underlying infection, sometimes by Epstein-Barr virus co-infection, not the drug. Stop every course at the first spot and you leave infections undertreated and hand the patient a lifelong allergy label they may not need. The opposite failure — ploughing through blistering, mucosal or feverish rash because "it is probably just amoxicillin rash" — is rarer but far more dangerous. Red flags mean stop and get urgent help. Everything else means one phone call before the next dose.
How can you tell if it is a true allergy later?
You cannot tell from the rash itself, and you cannot tell today. What settles the question is penicillin skin testing, done by an allergist once the skin has completely cleared — no residual pink, no itching, no antihistamines for 3–5 days beforehand. The test uses two reagents: a major determinant (penicilloyl-polylysine, sold as Pre-Pen) and a minor determinant mixture, plus amoxicillin itself. A wheal of 3 mm or more over the saline control at 15 minutes is a positive. Roughly 90% of people carrying a penicillin-allergy label in their chart test negative, per CDC estimates, which tells you how unreliable the label usually is.
Timing matters more than most referral letters admit. The sweet spot is 4–6 weeks after the reaction resolves. Test sooner and you risk a false negative while the immune system is still in flux; wait a year and sensitivity fades, so a genuinely allergic patient can slip through. If skin testing is negative, the next step is a direct oral amoxicillin challenge — 250 mg, then a full dose an hour later, supervised in a clinic with epinephrine and resuscitation equipment within arm's reach. That is not theatre. It is the only way to confirm tolerance with certainty, and it converts a lifetime of second-line antibiotics into a normal prescription.
What testing cannot do
Skin testing covers IgE-mediated reactions — the ones that appear within 1–6 hours of a dose, and always within 72 hours. It does not reliably detect the delayed T-cell reactions that produce most amoxicillin rashes, including the maculopapular eruption your child probably has right now. A negative skin test plus a passed oral challenge still leaves a small residual risk for a serious delayed reaction such as DRESS, SJS/TEN or AGEP, which is why the challenge is conducted in a monitored setting and why you watch for the first 48 hours after. If you had mucosal involvement, blistering, facial swelling or a fever above 38°C (100.4°F) during the original reaction, skip the challenge pathway entirely and let the allergist decide — some of those patients go straight to a graded desensitisation protocol in hospital or avoid beta-lactams permanently.
One practical point: ask for the results in writing, with the specific drug and dose tested. "Penicillin allergy" written in a chart without qualification follows people for decades and pushes them onto broader-spectrum antibiotics, which carry their own resistance and side-effect costs. Most people labelled penicillin-allergic — again, roughly nine in ten — can safely take penicillins after evaluation, and the appointment is worth the six-week wait.
What should you do if you are not sure and cannot reach a doctor?
It is 9 p.m., the rash appeared this afternoon, and the on-call line is ringing out. Work through red flags first, in this order: any blistering or peeling skin, sores or raw patches in the mouth, eyes or genitals, skin that hurts to touch, fever above 38°C (100.4°F), facial or tongue swelling, wheezing, or a child who is drowsy, confused or floppy. Any one of those means the emergency department, not a wait-and-see approach. Do not drive yourself if you are the patient and you feel unwell, and do not give another dose on the way.
With no red flags, the safer default is to hold the next dose and call the prescriber or an advice line as soon as it opens. Holding one dose of amoxicillin rarely changes the outcome of a routine ear infection or chest infection, and it buys a clinician the chance to see the rash in its early state rather than through a phone description. If the rash is itchy but the child is otherwise well, playing, drinking and afebrile, some clinicians will tell you to continue the course and document the rash. Get that instruction from a person, not from a search result.
Do not reach for leftover antibiotics from a previous illness, and do not let a pharmacist swap you onto another penicillin-family drug such as Augmentin or a cephalosporin without a prescriber's input. Cross-reactivity estimates between penicillins and later-generation cephalosporins sit around 1-2% for most agents, but that number is irrelevant if nobody has assessed what kind of rash you are looking at. Antihistamines such as cetirizine or loratadine ease itch and are widely used for benign delayed rashes, though the evidence for them is modest and they do nothing for the underlying reaction. Give one only if a clinician has approved it, and never use sedation to mask a child who is getting worse.
Write down the clock time of the first dose that triggered the rash, the time the rash appeared, and the exact drug name and dose. That single note is what an allergist needs six weeks from now to decide between skin testing and a direct oral challenge, and roughly 90% of people carrying a penicillin allergy label turn out on testing not to be allergic at all. A vague "she reacted to amoxicillin once" in a chart costs years of second-line antibiotics.
What happens if you stop amoxicillin too soon?
Stopping mid-course is not a neutral act. For group A streptococcal pharyngitis, the classic 10-day penicillin course exists for one reason: it takes roughly that long to eradicate the organism from the pharynx, and eradicating it is what prevents acute rheumatic fever. Quit on day four and the sore throat may well be gone, but the immune cross-reaction that damages heart valves is still on the table. Rheumatic fever is rare in the US and Western Europe, which is why parents there are often casual about it, but it is the reason the World Health Organization still pushes full courses in settings where it is common, and it is not a complication anyone wants to explain to a cardiologist ten years later.
Then there is the resistance argument, and it is stronger than most people assume. Sub-therapeutic exposure, which is what stopping early creates, is precisely the condition that selects for partially resistant bacteria. The standard estimate is that roughly 30 to 50 percent of antibiotic use in humans is unnecessary or incorrectly dosed, and every truncated course is a small experiment in Darwinian selection run at population scale. Middle ear infections and sinusitis can also rebound after a few days of improvement: the fluid and inflammation settle, the drug stops, and the surviving bacteria regrow with less competition.
If the rash turns out to be a true allergy and amoxicillin has to go, the replacement is rarely free of cost. Cephalosporins cross-react with penicillins at a low but non-zero rate, and clindamycin, a common substitute, carries a Clostridioides difficile risk several times higher than amoxicillin's. Azithromycin is easier to take but pneumococci in many regions are now resistant to it. Macrolide resistance in Streptococcus pneumoniae has been measured above 30 percent in parts of East Asia. Swapping drugs is sometimes necessary; it is not a good default.
The practical rule for the next hour is this: unless the rash came with any red-flag feature, keep giving the doses on schedule and get the rash looked at within a day or two rather than stopping on your own. The one legitimate reason to stop immediately is a red flag, and in that case you are not managing the rash at home, you are on the way to being seen. Everything else can wait for a clinician who can look at the skin and decide.
Frequently Asked Questions
Can amoxicillin cause a rash without allergy?
Yes. Roughly 5-10% of children taking amoxicillin develop a maculopapular rash that has nothing to do with IgE-mediated allergy. It usually appears on day 5 to 10 of treatment, often alongside a viral infection such as Epstein-Barr virus, and it is the infection plus the drug together, not the drug alone, that triggers it. Most of these children can take amoxicillin again later without reacting.
How long after taking amoxicillin does an allergic rash appear?
It depends on the type of reaction, and the timing is the single most useful clue you have. Immediate IgE reactions show up 1-6 hours after a dose, usually as hives. Severe delayed reactions such as DRESS or Stevens-Johnson syndrome can take 2-8 weeks. The common benign rash appears at 5-10 days. A reaction on day 7 looks nothing like a reaction at hour 2.
What does a penicillin allergy rash look like?
True penicillin allergy usually produces urticaria: raised, itchy wheals with pale centres and red margins, sometimes with angioedema of the lips, eyelids or hands. Urticaria moves around and each individual wheal fades within 24 hours. The dangerous exception is blistering or peeling skin with involvement of the mouth, eyes or genitals, which is a medical emergency, not a wait-and-see rash.
Should I stop amoxicillin if my child gets a rash?
Do not stop on appearance alone. Stop immediately and seek emergency care if there is facial swelling, breathing difficulty, blistering, peeling skin, mucosal sores, or a fever with widespread rash. Otherwise, call the prescriber before stopping, because undertreated infection, especially strep or pneumonia, carries more risk than a benign rash. Roughly 90% of children labelled penicillin-allergic are not allergic on formal testing.
Can a rash from amoxicillin be treated while continuing the antibiotic?
Sometimes. If the rash is mild, non-urticarial, and there are no red flags, a clinician may continue the amoxicillin and add a non-sedating oral antihistamine such as cetirizine at 10 mg once daily for an adult, with review within 24-48 hours. This happens only with medical approval and only when the infection genuinely needs that specific drug. Hives, swelling or any systemic symptom means stopping.
How can I tell if my rash is from amoxicillin or something else?
Work through three things: timing, appearance, and other symptoms. A flat, blotchy rash on day 6 of treatment in a child with a sore throat points to a viral or non-allergic drug rash; hives within 2 hours of a dose point to IgE allergy. If it matters, an allergist can do skin prick and patch testing roughly 4-6 weeks after the rash clears, when the reaction has settled.